Showing posts with label why it works?. Show all posts

Saturday, April 2, 2016

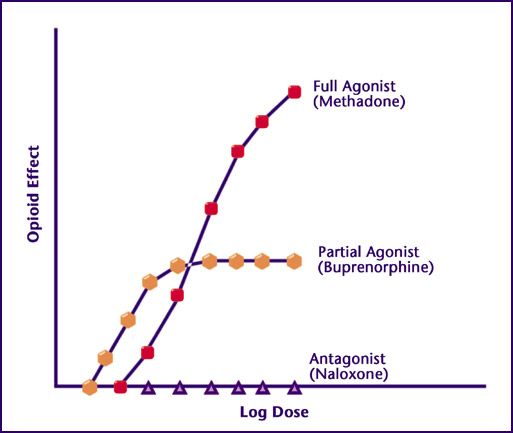
full agonists vs partial agonists

Definition by Wonder Me!:
Full agonists activate maximum effects when binding to receptors.
Partial agonists activate less than maximum effects when binding to receptors

Clinical example:
Methadone, like heroin, is the full agonist for opioid effects
Buprenorphine as the partial agonist for opioid effects

Why it works?:
"For people who are not addicted to or dependent on opioids, the effects of partial (buprenorphine) and full (methadone) agonists are indistinguishable. However, at a certain point, the increasing effects of partial agonists reach maximum levels. For this reason, people who are dependent on high doses of opioids are better suited to treatment with a full agonist, such as methadone." (1)


References:

Pharmacologic antagonist

Definition by Wonder Me!: 
Pharmacologic antagonist binds the receptors. It doesn't make the receptor do anything. It just blocks the receptor from doing anything the receptor is supposed to be activated to do because the pharmacologic antagonists block the receptors preventing other agonists to bind to the receptors to activate the receptors to do anything.

Clinical example:
Propranolol (nonselective β1 and β2) 

Why it works?
"Beta blockers work by blocking the effects of the hormone epinephrine, also known as adrenaline. When you take beta blockers, the heart beats more slowly and with less force, thereby reducing blood pressure. Beta blockers also help blood vessels open up to improve blood flow." (1)


Citations:
(1)  http://www.mayoclinic.org/diseases-conditions/high-blood-pressure/in-depth/beta-blockers/art-20044522


competitive antagonists

Definition by Wonder Me!: 
Competitive antagonists have to compete with other agonists for receptors. And, once it already binds to the receptors, it still can be replaced by agonists if the agonists concentration is high enough to displace competitive antagonists.


Clinical example:
Naloxone(1)


Why it works?: 
Naloxone is an infusion because it has short half-life. Thus, at first, its concentration exceeds opioid concentration. But then, due to its short half-life, its concentration becomes less than that of opioid. This makes pt becomes unconscious again. Therefore, constant naloxone drip is needed. (2)  


MCQ resources:


Citations:

irreversible antagonist

Definition by Wonder Me!:
Irreversible antagonists bind permanently to receptors. Therefore, even if you put a bunch of agonists to bind to these receptors, these irreversible antagonists won't leave these receptors for the agonists to bind to these receptors.


Clinical example:
- Phenoxybenzamine (at alpha1-adrenoreceptors meaning alpha-1-antagonist!) (1)


Why it works? :
- Phenoxybenzamine permanently binds to alpha adreno-receptors.  Thus, it disables alpha adreno-receptors. Therefore, it helps in Reynauld's disease & HTN caused by phaeochromocytoma (2).

- In Reynauld's disease, "the local fault may involve the alpha 2-adrenergic receptors, which are most important in reflex sympathetic vasoconstriction."  (3)

- "A pheochromocytoma is a rare, catecholamine-secreting tumor that may precipitate life-threatening hypertension." (4) Circulating catecholamines include epinephrine and norepinephrine. These catecholamines cause "vasoconstriction in most systemic arteries and veins (postjunctional α 1 and α 2 adrenoceptors)" (5)


Citations:
(1) https://books.google.com/books?id=ThlamNsTDnMC&pg=PA104&dq=%22irreversible+antagonist%22+examples&hl=en&sa=X&ved=0ahUKEwj__YPH1PHLAhXEtIMKHVVlBNwQ6AEIOjAF#v=onepage&q=%22irreversible%20antagonist%22%20examples&f=false

(2) https://books.google.com/books?id=F4-IdTewurIC&pg=PA280&lpg=PA280&dq=%22irreversible+antagonist%22+phenoxybenzamine&source=bl&ots=mRnuVNefvI&sig=dL42U7HMA5HCMY7jA7M4hOP4NfI&hl=en&sa=X&ved=0ahUKEwjUp_im1vHLAhWMuoMKHVwuArcQ6AEIUzAG#v=onepage&q=%22irreversible%20antagonist%22%20phenoxybenzamine&f=false

(3) http://www.ncbi.nlm.nih.gov/pubmed/2022404

(4) http://emedicine.medscape.com/article/124059-overview

(5) http://www.cvphysiology.com/Blood%20Pressure/BP018.htm 

Friday, April 1, 2016

Na 135-145mEq/L

The normal range for blood sodium levels is 135 to 145 milliequivalents per liter (mEq/L).

Why it works?
In lab, they put in something that binds with sodium to detect sodium. Why? 9g of NaCl is not 4.5g of Na and 4.5g of Cl. Why not? Remember the molecular weight of Na is 23g and Cl 35.5g. Therefore, to really know how much Na there is, it's hard to get it straight from blood. Why hard? blood contains many things like albumin, lipid, etc., Therefore, need to have a reagent that specifically binds to Na to really measure Na in blood. Therefore lab value for Na in blood is reported as mEq because 1 reagent:1Na molecule. 

Note that 0.9%NaCl is 9g of NaCl in 1L of the entire solution. Also note that mEq in Normal Saline "contains 154 mEq/L sodium and 154 mEq/L chloride." (per http://www.rxlist.com/normal-saline-drug.htm). So that means NS is slightly more salty than Na level in blood. Then, why would you give NS? well, if you're not too dehydrated, then NS is fine but if you have kidney failure with dehydration, NS is not sooooo good for u because it's quite salty. 


 Wait, but you thought NS is isotonic solution? It is! It is isotonic because it's equivalent to the entire blood (remember blood has many other solutes other than just Na). So.... => Dextrose 5% 1/2NS is really the isotonic with less sodium levels than blood => that's why it's so popular.


~Wonder Me! 

Thursday, March 31, 2016

Cholesterol or lipid profile


Mini-Case*: Patient - My cholesterol is 295.... Don't remember what type of cholesterol. Aren't they all the same?

Thinking: Cholesterol values include Total cholesterol, LDL, HDL, VLDL, which one? What is what?
=> Conclusion: most likely to be 'Total cholesterol' if pt only can only report 1 # but not any other #'s.


Case*: Pt is 50y/o with diabetes. Which Cholesterol level to start on Simvastatin?
Answer: Cholesterol level doesn't matter. No need to obtain lipid panel test. Just start them on Simvastatin.

Case*:  Pt asks How does Simvastatin affect HDL and LDL?
Answer: Lower LDL but very miniscule effects on HDL


Why it works?

Blurb:


  • Total cholesterol
  • LDL (bad) cholesterol--the main source of cholesterol buildup and blockage in the arteries
  • HDL (good) cholesterol--helps keep cholesterol from building up in the arteries
  • Triglycerides--another form of fat in your blood

  • What is total cholesterol?

    Total Cholesterol (done by enzymes, measured directly from blood):  Total cholesterol can be measured directly from blood. Enzyme (cholesterol oxidase) is added to produce reaction byproducts, H2O2.  Enzyme (Peroxidase) is then added to produce color. This color is electromagnetically analyzed at 500nm. The intensity of this color is directly proportional to cholesterol concentration.

    Triglycerides (done by enzymes, measured directly from blood) - must be fasting for correct level of triglycerides

    HDL (done by special agents, measured directly from blood, read by color intensity produced from electromagnet)

    LDL: very expensive to measure directly from blood via ultra-centrifuge. So, use Friedwald equation (only correct if pt is fasting)

    LDL-Cholesterol: Most of the circulating cholesterol is found in three major lipoprotein fractions: very low density lipoproteins (VLDL), LDL and HDL.
    [Total chol] = [VLDL-chol] + [LDL-chol] + [HDL-chol]

    LDL-cholesterol is calculated from measured values of total cholesterol, triglycerides and HDL cholesterol according to the relationship: 
                              [LDL-chol] = [total chol] - [HDL-chol] - [TG]/5
     where [TG]/5 is an estimate of VLDL-cholesterol and all values are expressed in mg/dL. 


    ~Miss Student

    *All cases are fictitious. No real patient encounters. Just my rich imagination! :)


    Read lab values:
    Mnemonics: High Healthy HDL; Low Let it down LDL ~Miss Student


    Nutrition:


    Diet restrictions: 
    1 - No Alcohol 24hrs before tests (elevate #)
    2 - No eating 12 hrs before tests (elevate triglycerides)
    3 - No water restrictions

    Clinical procedure:
    - Blood lab test (venipuncture)
    - Red tube (fasting)

    Who should be screened?:
    In priority order:

    1. - All men over 35 y/o even in absence of any risk factors for CHD
    2. - Men & women >20 y/o with increased risks for coronary heart disease (CHD)
    Increased risk, for the purposes of this recommendation, is defined by the presence of any one of the risk factors listed below. The greatest risk for CHD is conferred by a combination of multiple listed factors.
    • Diabetes.
    • Previous personal history of CHD or non-coronary atherosclerosis (e.g., abdominal aortic aneurysm, peripheral artery disease, carotid artery stenosis).
    • A family history of cardiovascular disease before age 50 in male relatives or age 60 in female relatives.
    • Tobacco use.
    • Hypertension.
    • Obesity (BMI ≥30).
    10-year CVD risk factors: http://cvdrisk.nhlbi.nih.gov/

    Helpful link:
    http://www.gpnotebook.co.uk/simplepage.cfm?ID=x20030114211535665170: short need-to-know details for lipid profile info.
    (2) http://www.cdc.gov/nchs/data/nhanes/nhanes_03_04/l13_c_met_lipids.pdf: how to calculate total cholesterol => not how total cholesterol is usu. obtained since you can do measure total cholesterol by hands
    http://www.wikihow.com/Calculate-Total-Cholesterol => how lipid panel is really measured
    http://www.uspreventiveservicestaskforce.org/Page/Document/RecommendationStatementFinal/lipid-disorders-in-adults-cholesterol-dyslipidemia-screening#consider

    Sunday, March 20, 2016

    cauliflower ear


    thompson test

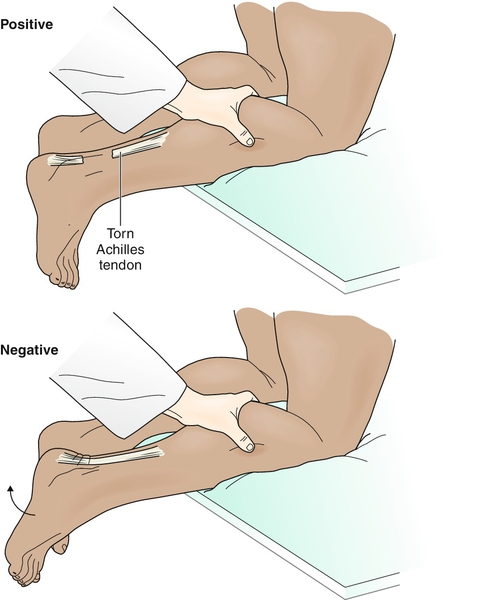
    Thompson's test: tests whether the Achille's tendon is intact. If the Achilles' tendon is intact, when the calf muscle is squeezed, the foot will plantar-flex. If the Achilles' tendon is ruptured, the foot will NOT plantar-flexed as the calf muscle is squeezed.


    Why it works? The soleus & gastrocnemius make up the calf muscles. Both of these 2 muscles attach to the Achilles' tendon. Therefore, when the you squeeze the calf muscles, you are trying to lift these 2 muscles up contracting the muscles leading to the plantar-flexion of the foot.


    Images:


    Video:

    Maisonneuve fx

    Maisonneuve fracture: Maisonneuve fracture is a fracture in the proximal fibula. It is usually overlooked since patient is more focused on the pain in the ankle than tenderness or pain in the proximal fibula. Check for maisonneuve fx for fx s/s in the ankle. (1)

    Why it works: Forceful external rotation & internal rotation of the ankle cause the separation of the distal edge of the fibula. Fibula is a long bone. As the distal edge is pulled away from the tibula, the part near the proximal end endures great stretch. As a lever, the part near the proximal end breaks away from the proximal end causing a fracture. (1)

    Case example: http://manuetcorde.org/2013/03/03/dr-maisonneuve-his-fracture-and-why-students-should-learn-their-eponyms/

    X-rays: http://radiopaedia.org/articles/maisonneuve-fracture

    Mechanism videos:


    ----
    Sources:
    (1) https://books.google.com/books?id=YmQ3GGGjDhMC&pg=PA646&dq=maisonneuve+fracture&hl=en&sa=X&ved=0ahUKEwjlzuDXgdDLAhXLJx4KHWGJDM44ChDoAQgpMAM#v=onepage&q=maisonneuve%20fracture&f=false)

    Friday, March 18, 2016

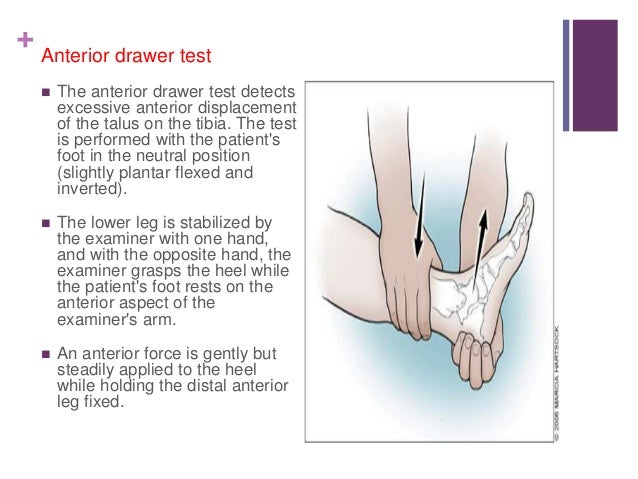
    Anterior drawer test

    Why it works?: Displaces the anterior talofibular ligament.


    Grey Turner's sign

    Gray-Turner's sign is a sign that indicates hemorrhage in the peritoneum. It is a bruise seen in the side of the abdomen (flank).  When pancreas enzymes got released into the retroperitoneal cavity, it  causes bleeding from the retroperitoneum to the subcutaneous tissues of the area between the the end of the rib cage and the ilium (hip bone), aka the flank area (1). Even tho it's commonly thought to be attributed to acute pancreatitis, it can also occurs in AAA (abdominal aortic aneurysm).

    Why it works?:
    In normal physiology: pancreas releases enzymes that dissolve fat and nutrients in the small intestines. Remember that the pancreas lies behind the stomach and in front of the spine, it is, therefore, a retroperitoneal organ. Also, remember that the pancreas releases enzymes to the duodenum which is the first part of the small intestine that connects directly to the stomach. Therefore, you can image how the pancreas releases enzymes directly into the intestines.

    In pancreatitis pathophysiology: pancreatic enzymes destroy the pancreas parenchyma and blood vessels. The damage of the blood vessels causes retroperitoneal hemorrhage.

    In pancreatitis, the anatomic pathways of the pancreatic hemorrhage: "hemorrhage originates from the anterior pararenal space => spreading to posterior renal fascia => then to the lateral edge of the quadratus lumborum muscle (flank wall structures).: "The lumbar triangle is a site of anatomic weakness"=> "structural predisposition" to hemorrhaging spreading (according to (2)).

    Mnemonics: Grey TURNer’s sign is located when you TURN towards your flank 


    -----
    Sources:
    1 - Clinical images of Gray Turner's & Cullen's signs: http://www.nejm.org/doi/full/10.1056/NEJMicm1504339

    2- Anatomic pathways: http://www.ncbi.nlm.nih.gov/pubmed/2910743

    Peritoneal anatomic pathways: http://pubs.rsna.org/doi/full/10.1148/rg.322115032

    Pancreatitis basic info. for patients from Nytimes: http://www.nytimes.com/health/guides/disease/acute-pancreatitis/overview.html

    Pancreas basic info. for patients from Hopkins pathology: http://pathology.jhu.edu/pc/BasicOverview1.php?area=ba

    Acute pancreatitis basic info.: http://drkupe.blogspot.com/2011/02/acute-pancreatitis.html

    Mnemonics: http://www.internalizemedicine.com/2012/01/grey-turners-sign-and-cullens-sign-mnemonic.html

    Retroperitoneal organs embryology development: https://academic.amc.edu/martino/grossanatomy/site/Medical/Lab%20Manual/Gastrointestinal/answers/mediastinum11.htm

    Retroperitoneal organs anatomy & pathophysiology lecture: http://www.slideshare.net/dhruvtaneja1/reproteritoneum-anatomy-and-pathology

    Chronic pancreatitis: http://www.ddc.musc.edu/public/diseases/pancreas-biliary-system/chronic-pancreatitis.html

    Murphy's sign

    Murphy's sign strongly indicates cholecystitis. However, the absence of Murphy's sign does not rule out cholescytistis (1). You can do this maneuver by having the patient take a deep breath in to push the diaphragm downward as you push your fingers up the lower costal margin in the midclavicular line trying to go below the liver. If patient stops breathing, it is positive, meaning the patient may have cholecystitis (2). Must confirm with lab and imaging.


    Why it works: Recall the location of the gallbladder: under the liver @ the midclavicular line. Since inflamed gallbladder (cholescystitis) causes gallbladder tenderness, the gallbladder being sandwiched between the downward pressure produced by the diaphragm and the hand pushing up, this maneuver produces pain and patient will stop breathing in to relieve pressure being pushed down on the poor gallbladder!

    See the anatomical position of gallbladder in relation to the costal margin and the liver:

    Sources:
    1: http://emedicine.medscape.com/article/171886-clinical#b3
    2: http://www.turner-white.com/pdf/hp_nov00_murphy.pdf
    3: gallbladder image with relation to skeleton, liver & other anatomical regions (highly accurate!): http://www.med.umich.edu/lrc/coursepages/m1/anatomy2010/html/clinicalcases/cholelithiasis/cholelithiasis.html