Showing posts with label pharmacology. Show all posts

Saturday, April 2, 2016

a curious case of full & partial agonists

Definition by Wonder Me!:
Partial agonists actually can block the effects of full agonists when dispersed together.

Clinical examples:

Nubain = partial agonist
Oxycodone = full agonist
=> Too much nubain => less receptors for oxycodone to bind => oxycodone can exert its effects that it usually can in the absence of nubain => reduced pain relief (1)


References:
(1) https://books.google.com/books?id=AniUCgAAQBAJ&pg=PA327&dq=oxycodone+nubain+agonist&hl=en&sa=X&ved=0ahUKEwjEhqO56fHLAhWEwYMKHUBiAW8Q6AEIHDAA#v=onepage&q=oxycodone%20nubain%20agonist&f=false

full agonists vs partial agonists

Definition by Wonder Me!:
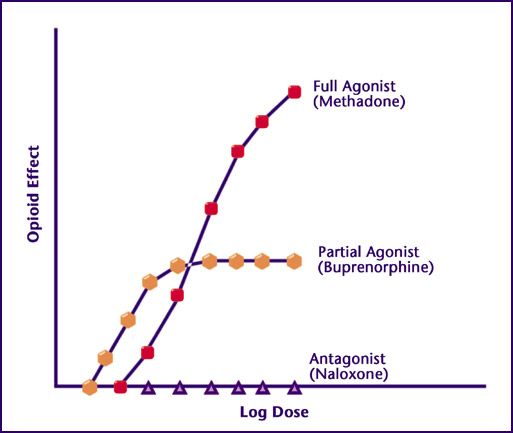
Full agonists activate maximum effects when binding to receptors.
Partial agonists activate less than maximum effects when binding to receptors

Clinical example:
Methadone, like heroin, is the full agonist for opioid effects
Buprenorphine as the partial agonist for opioid effects

Why it works?:
"For people who are not addicted to or dependent on opioids, the effects of partial (buprenorphine) and full (methadone) agonists are indistinguishable. However, at a certain point, the increasing effects of partial agonists reach maximum levels. For this reason, people who are dependent on high doses of opioids are better suited to treatment with a full agonist, such as methadone." (1)


References:

antagonists

Definition by Wonder Me!:
Antagonists bind to receptors blocking it from binding with agonists to produce any effects.


Pharmacologic antagonist

Definition by Wonder Me!: 
Pharmacologic antagonist binds the receptors. It doesn't make the receptor do anything. It just blocks the receptor from doing anything the receptor is supposed to be activated to do because the pharmacologic antagonists block the receptors preventing other agonists to bind to the receptors to activate the receptors to do anything.

Clinical example:
Propranolol (nonselective β1 and β2) 

Why it works?
"Beta blockers work by blocking the effects of the hormone epinephrine, also known as adrenaline. When you take beta blockers, the heart beats more slowly and with less force, thereby reducing blood pressure. Beta blockers also help blood vessels open up to improve blood flow." (1)


Citations:
(1)  http://www.mayoclinic.org/diseases-conditions/high-blood-pressure/in-depth/beta-blockers/art-20044522


competitive antagonists

Definition by Wonder Me!: 
Competitive antagonists have to compete with other agonists for receptors. And, once it already binds to the receptors, it still can be replaced by agonists if the agonists concentration is high enough to displace competitive antagonists.


Clinical example:
Naloxone(1)


Why it works?: 
Naloxone is an infusion because it has short half-life. Thus, at first, its concentration exceeds opioid concentration. But then, due to its short half-life, its concentration becomes less than that of opioid. This makes pt becomes unconscious again. Therefore, constant naloxone drip is needed. (2)  


MCQ resources:


Citations:

irreversible antagonist

Definition by Wonder Me!:
Irreversible antagonists bind permanently to receptors. Therefore, even if you put a bunch of agonists to bind to these receptors, these irreversible antagonists won't leave these receptors for the agonists to bind to these receptors.


Clinical example:
- Phenoxybenzamine (at alpha1-adrenoreceptors meaning alpha-1-antagonist!) (1)


Why it works? :
- Phenoxybenzamine permanently binds to alpha adreno-receptors.  Thus, it disables alpha adreno-receptors. Therefore, it helps in Reynauld's disease & HTN caused by phaeochromocytoma (2).

- In Reynauld's disease, "the local fault may involve the alpha 2-adrenergic receptors, which are most important in reflex sympathetic vasoconstriction."  (3)

- "A pheochromocytoma is a rare, catecholamine-secreting tumor that may precipitate life-threatening hypertension." (4) Circulating catecholamines include epinephrine and norepinephrine. These catecholamines cause "vasoconstriction in most systemic arteries and veins (postjunctional α 1 and α 2 adrenoceptors)" (5)


Citations:
(1) https://books.google.com/books?id=ThlamNsTDnMC&pg=PA104&dq=%22irreversible+antagonist%22+examples&hl=en&sa=X&ved=0ahUKEwj__YPH1PHLAhXEtIMKHVVlBNwQ6AEIOjAF#v=onepage&q=%22irreversible%20antagonist%22%20examples&f=false

(2) https://books.google.com/books?id=F4-IdTewurIC&pg=PA280&lpg=PA280&dq=%22irreversible+antagonist%22+phenoxybenzamine&source=bl&ots=mRnuVNefvI&sig=dL42U7HMA5HCMY7jA7M4hOP4NfI&hl=en&sa=X&ved=0ahUKEwjUp_im1vHLAhWMuoMKHVwuArcQ6AEIUzAG#v=onepage&q=%22irreversible%20antagonist%22%20phenoxybenzamine&f=false

(3) http://www.ncbi.nlm.nih.gov/pubmed/2022404

(4) http://emedicine.medscape.com/article/124059-overview

(5) http://www.cvphysiology.com/Blood%20Pressure/BP018.htm 

first pass effects


Physiologic antagonist

Definition (by Wonder Me!):
Physiologic antagonist is an antagonist so-called because it doesn't exert its antagonistic effects directly on the receptor that produces the effects. Physiologic antagonists bind to a receptor and makes that receptor creates an effect that is opposite to the other receptor.


Clinical implications: Antidotes!


Clinical examples:
- Epinephrine for antihistamine effects:
"There are several substances that have antihistaminergic action despite not being ligands for the histamine receptor. For instance, epinephrine raises arterial pressure through vasoconstriction mediated by A1-adrenergic receptor activation, in contrast to histamine, which lowers arterial pressure. Thus, despite not being true antihistamines because they do not bind to and block the histamine receptor, epinephrine and other such substances are physiological antagonists to histamine." (1)


 - Glucagon for betablockers overdose:
"Glucagon has become an accepted antidote to beta-blocker poisoning because it stimulates cAMP synthesis independent of the beta-adrenergic receptor.[41] Glucagon has shown positive inotropic and chronotropic effects despite beta-receptor blockade in numerous animal models and in humans." (2)
 - Adrenaline & insulin on blood sugar (3)
- Carbachol & papaverine on smooth muscles (3)
- Noradrenaline & histamines on allergic conditions (3)


Citation:
(1) https://en.wikipedia.org/wiki/Physiological_agonism_and_antagonism
(2) http://www.medscape.com/viewarticle/430202_6
(3) https://books.google.com/books?id=X3cCZQCrrjcC&pg=PA43&lpg=PA43&dq=%22Physiologic+antagonist%22+examples&source=bl&ots=SxQy6ELxCI&sig=fuqUEwMnO93e_fwrCwTgoRUwPOo&hl=en&sa=X&ved=0ahUKEwj4hc-y0fHLAhXqyIMKHeV0BiEQ6AEIOjAF#v=onepage&q=%22Physiologic%20antagonist%22%20examples&f=false

Friday, April 1, 2016

Pharm basics

I - PK (Pharmaco-Kinetics):
1. ADME: Absorption, Distribution, Metabolism, Excretion
2. Absorption mechanism: pinocytosis, passive diffusion, active transport, facilitated diffusion
3. Terms:
     Bioavailability = %[drug]systemic circulation
     Bioequivalence = same AUC (Cmax, Tmax)
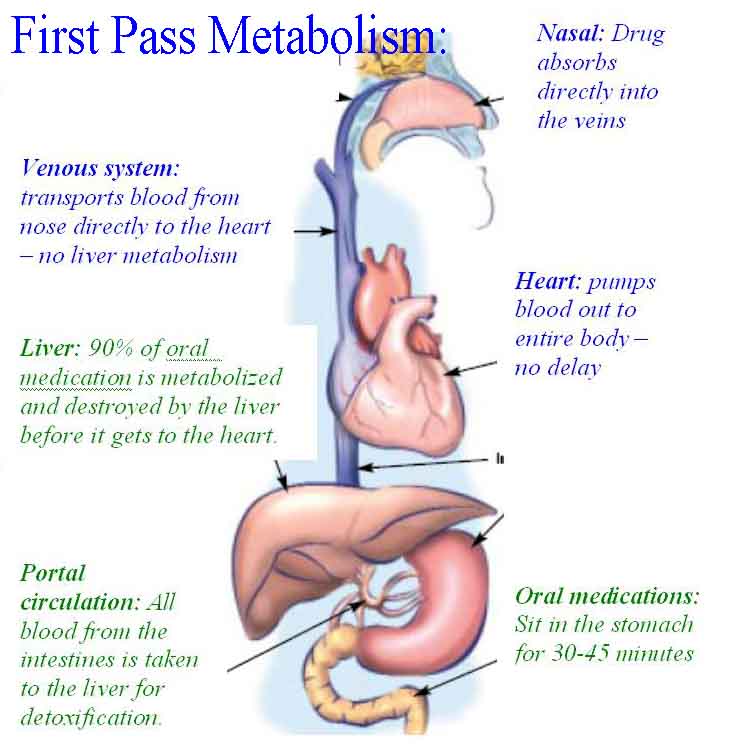
     First-pass effect = oral then after liver
     Volume of distribution = dose/[plasma concentration]
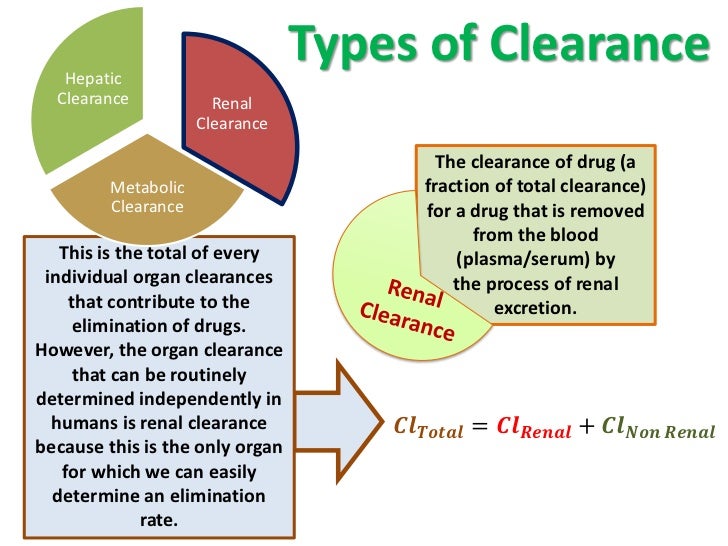
     Clearance = t(totally eliminated)
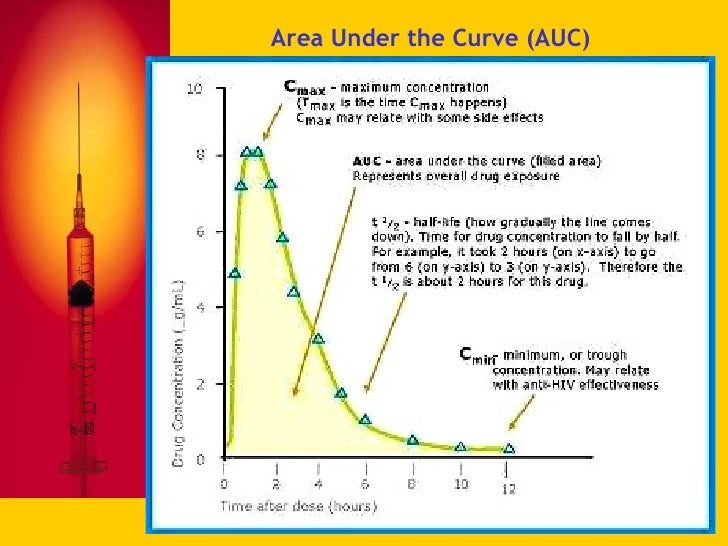
     Area under the Curve (AUC) = Cmax, total T(drug exposure)
     Cmax = max [drug]blood (i.e., max drug conc. in blood)
     Tmax = time 'til Cmax (i.e. time it takes for Cmax to occur)
     Half-life (t1/2) = time until 50% of drug is eliminated from body
            Steady state: 3-5 half-lives
            Elimination time: 4-5 half-lives

II - PD (Pharmaco-Dynamics):
1. Receptor types:
      a. Gated-ion channels: agonist => opens channels. Ex: ACh (Nicotinic), GABA (anti-stress, anti-anxiety), 5-HT (serotonin - antidepressant)
      b. G-protein coupled: α, β adrenergic
      c. Transmembraneous: insulin, peptide
      d. Intracellular: sex hormones, glucocorticoids

2. Drug - receptor interactions:
      a. affinity: strength of binding to receptors
      b. potency: high potency = lower dose for effects
      c. efficacy: high efficacy = 

3. Drug dose:
      a. ED50: effective dose in 1/2 of pts
      b. TD50: toxic dose in 1/2 pts
      c. LD50: lethal dose in 1/2 pts
      d. TI = TD50/ED50: therapeutic index

4. Agonist:
      a. Full: full effects
      b. Partial: less than full effects
      c. Full agonist + partial agonist = partial acts as INHIBITOR

5. Antagonist:
      a. Pharmacologic: binds to block receptors. Ex: propanolol as beta-blockers
      b. Competitive: replace-able if higher conc. of agonist. Ex: naloxone for opioid receptors
      c. Irreversible: non-replace-able even if higher conc. of agonist. Ex: Phenoxybenzamine as adreno-receptors antagonists.
      d. Physiologic: binds to opposite receptors to produce opposite effects. Ex: epinephrine for antihistamines effects

III - Adverse Drug Reactions: 
1. Drug-drug
2. Dose-related
3. Disease-related
4. Side effect
5. Intolerance (sensitivity)
6. Toxicity
7. Drug allergies

IV - Scheduled drugs:
1. Schedule I: nobody can prescribe, highest abuse Ex: heroin, Marijuana, LSD, Peyote, Ecstasy, Quaalude
2. Schedule II: hand-delivered paper signature prescriptions Ex: Vicodin, cocaine
3. Schedule III: fax prescription Ex: codeine/acetaminophen, anabolic steroids (oxa-drolone), didrex (benzphatamine), oral marinol.
4. Schedule IV: fax prescription Ex: tramadol, sleeping pills (bensolam, ambien), BZD (valium), soma, etc.
5. Schedule V: fax prescription Ex: Lomotil, Phenergan with Codeine, Robitussin with codeine, AED (vimpat, Lyrica, ezogabine)
6. CURES: II, III, IV drug registry in California

V - Prescription Writing:
1. sig., #refills, DAW?
2. Do NOT use list

VI - FDA Drug approval process:
1. Discovery
2. Animal-testing
3. Clinical trials:
      a. Phase 1: 20-100 healthy persons (PK)
      b. Phase 2: 100-200 target disease pts (efficacy, not by chance)
      c. Phase 3: 1000's target disease pts (safety for lots, not just efficacy)
      d. Phase 4 (optional): 100,000 target disease pts (maybe some bad side effects in phase 3, not known long enuf in phase 3, most likely the public will be unlikely to use it ...)
4. Post-marketing surveillance:
      a. REMS: FDA programs to ensure drug use is approrpiate (Mifeprex, Acne drug)
      b. MedWatch, 'Dear Heath Care Professionals' letters: Auvi-Q, certain albuterol inhalers

VII - Drug names:
1. Chemical: IUPAC
2. Generic: 1 for all various brand-name
3. Trade: brand names

VIII - Drug development history:
1. Pure food & drug act: bans adulteration/mislabeling
2. Food, Drug, Cosmetic act: requires tests safety & purity
3. Kefauver-Harris: requires efficacy
4. Abuse prevention: requires scheduled
5. Poison prevention: requires child-resistant
6. Orphan: incentives for rare-disease drugs
7. Prescription marketing: bans drug samples sales
8. Dietary supplement: non-FDA regulated supplements
9. FDA ammendments: FDA regulates drug commercials
10. FDA innovation: FDA accelerates break-thru & fast-track drugs


Resources:
MCQ:
http://accesspharmacy.mhmedical.com/book.aspx?bookid=1576
 
http://global.oup.com/uk/orc/pharmacy/ifp_therapeutics/student/mcqs/ch01/

http://media.pharmacologycorner.com/wp-content/uploads/2009/01/usmle-pharmacology-quiz-multiple-choice.pdf

https://archive.org/stream/1GeneralPharmacologyMCQS/1%20General%20Pharmacology%20MCQS_djvu.txt

https://books.google.com/books?id=QlTUZH39lTYC&pg=PA13&lpg=PA13&dq=bioavailability+mcq&source=bl&ots=d9ocUgGr7A&sig=V5RMoGouHB0Yevpv2ztcsUkOC0s&hl=en&sa=X&ved=0ahUKEwi41O7MxvHLAhWru4MKHRHAATQQ6AEIMjAD#v=onepage&q=bioavailability%20mcq&f=false 


https://books.google.com/books?id=7PXn6BVhtT0C&pg=PA9&dq=%22competitive+antagonist%22+naloxone&hl=en&sa=X&ved=0ahUKEwjJqOTP2_HLAhUKlYMKHTFACO0Q6AEIJTAA#v=onepage&q=%22competitive%20antagonist%22%20naloxone&f=false


http://glutxi.umassmed.edu/documents/PharmacoDynamics.pdf
~Wonder Me


Clearance


PK vs PD


Thursday, March 31, 2016

Volume of distribution

Tho it is NOT  true, try to think of Vd simply reflects the volume of drugs dispersed into body tissues.
However, in fact,  grams of drugs/Vd = grams of drugs/plasma volume = plasma concentration
Therefore => Vd = grams of drugs/plasma concentration 
=> Vd = is a proportionality factor, not a physiologic factor (2) 
=> The amount of solution/solvent a drug needs to dissolved into to reach similar concentration of its concentration in plasma

Why does it matter? We need to know the Vd in order to calculate the desired loading dose (grams or mg) so that we can have the DESIRED drug concentration in the plasma.

What Vd is really, like really? "The volume of distribution is the theoretical size of the compartment necessary to account for the total drug amount in the body if it were present throughout the body in the same concentration found in the plasma." (1)

Sooo weird, like you have to know Vd to calculate the necessary dosage, then why how could the pharmacist figure out the Vd? They do that empirically I suspect by calculating the plasma concentration and the dosage given and then keep an index of these #'s (3) (after Wonder Me! googled a lot with key words such as how pharmacists calculate necessary volume of distribution, it linked me to a NAPLEX book. So helpful!)

Clinical examples:
- Digoxin must get into myocardial tissue with several compartments, what do you think its Vd wold be? Massive! (lots to get into tissue-binding)
- Warfarin must stay in the blood (think: blood thinner! must stay in the blood to 'thin' blood!) => therefore it has a small loading dose (think: you don't want to give too much of a drug directly to the blood stream when it likes to stay in the blood and doesn't want to go anywhere else. Meaning it doesn't need to that much to get to be highly-concentrated in the blood!) => Needless to say it has a small Vd. 
- Understanding Vd will help you get the desired Loading dose correctly!

- (4): 
DrugVD
Warfarin8L
Reflects a high degree of plasma protein binding.

Theophylline, Ethanol30L
Represents distribution in total body water.

Chloroquine15000L
Shows highly lipophilic molecules which sequester into total body fat.

NXY-0598L
Highly charged hydrophilic molecule.


Blurb:
- Vd simply reflects the volume of drugs dispersed into body tissues. (NOT true)
- High protein-bound (think Albumin in blood, think circulation and plasma, think big huge protein-drug complex unable to cross blood stream to leak into intracellular or interstitial fluid) drugs => Low Vd
- High tissue-bound drugs => high Vd
- High Vd => low plasma concentration
- Low Vd => high plasma concentration


This means the higher Vd, the higher the amount of drugs binding to body tissues and lower the amount of drugs 'swimming' freely in the blood plasma.
This means the small Vd will have a high initial concentration as the drug just enters the plasma content but then it will become smaller in concentration.
This means that the large Vd will have a low concentration (all drugs dispersed into the tissues).

Helpful interactive site to illustrate this concept: http://www.icp.org.nz/icp_t3.html

~Wonder Me

Citation:


Wednesday, March 30, 2016

Tmax, Cmax, Half life

All cases are fictitious, no real-life encounters. Imaginary cases! 

Case: alcoholic withdrawal & anxiety => 2mg Ativan IV (big dose!) => neuro depression then resp. depression => given 1hr ago => pt says now I'm still nervous as crazy (Tmax = 0.5, half life 4-6 hrs => fictitious )=> give him Ativan again? Pt went thru Tmax and Cmax and still not sedates him, even tho half life is really long => give more? =>okay to give a little more but not too much => titrate.
For some ppl used to Ativan who's very anxious and used to Activan => 2mg didn't touch him => may be able to give more than 1mg => actually u need to give like another 2mg.


~Miss student

loading dose

All cases are fictitious, no real-life encounters. Imaginary cases! 

Case: pt: I don't want to wait 3-5 days for Claritin 5mg for me to go to parent's house which has a dog that I'm allergic to. What can I do? NP: Start pt on loading dose and then start on regular min dose. However, this is NOT a good thing to do & this is not a good thing to do to the body since the body doesn't like to go to extreme. So, only do loading dose when ER!

Case: pt comes in w/

Loading dose is usually done by the pharmacist in Hospital for the calculation.

Ideal drug: short half life for loading dose. If it's not good, just stop it and let it go out of the body very quickly. Go too much => get rid quickly and easily. Ideal is meds is IV bc 100% bioavailibitliy, short-half-life => even w/ allergies => still good => come out quickly.

~Miss Student


Tuesday, March 29, 2016

HALF-LIFE

- Need to know half-life so that you won't over-dosing your patient. This is bc a drug w/ a long half-life will build up to toxic level if you keep giving too much too frequent. However, a drug with a short half-life needs to be given more frequent.


-Lithium half life 24 hrs, given once a day; => pt misses a dose; take 2 pills? no! problem? no!
-All drugs reach steady state in 3-5 half life's.
-If a drug has 2hr half life, how many half life does it take to go to 1/4? => 2 half life
-half life amount: 1/2 (1hl), 1/4 (2hl), 1/8 (3hl), 1/16 (4hl), 1/32 (5hl), 1/64 (6hl), 1/128 (7hl)
-if a drug has 1hr half life, pt misses the dose, frequency is every 6 hrs, => doesn't mean u should double the dose => it just tells you that you'd better not miss it. Probably good for ICU, probably not for home use.
- You don't want to check the level until it reaches until it reaches the steady state.
- You also don't want to change the dose until it reaches the steady state. Ex: Felbamate for anti-epileptics.
- Half life for Claritin is 8-11hrs (http://www.rxmed.com/b.main/b2.pharmaceutical/b2.1.monographs/CPS-%20Monographs/CPS-%20(General%20Monographs-%20C)/CLARITIN.html
) => Patient: I need to go to my parent's house and they have a dog and I'm allergic to dogs. I took the Claritin the day I go to my parents and it didn't work => NP: you need to take Claritin 3-5 days before you go to your parents to make sure it works.


Case: ICU pt 240BP=> long half life med  such as amlodipine - calcium channel blocker med which has 30-50 half life (but good for inpatient)? No, IV fast and short half life => give every hr so it's at steady state very quickly. Reach steady state pretty quickly => ideal BP. Too much meds, very sensitive pt => goes down too low => stop BP meds => how long does it take for the pt to get out of the system => takes more than 3-5 half life to go back.

Case: 24mg Amlodipine for 80y/o in regular hospital floor  from 200mmHg down to 70mmHg bc it's good for outpatient use => terrible drug for ER since it takes a long time to get rid of from the body since it's takes so long => do NOT use long half life but good for short half life drug.


~Miss Student


AUC

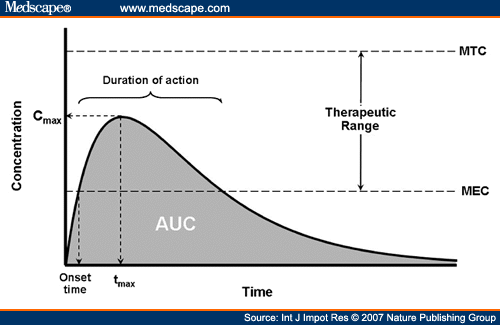
AUC: gives you Cmax & Clearance time ~Wonder Me


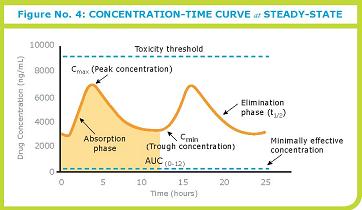
Pharmacokinetic parameters describing a typical plasma concentration time profile after an oral administration. Cmax, maximum concentration; tmax, time to Cmax; AUC, area under the curve; MEC, minimum effective concentration; MTC, maximum tolerated concentration.


Cmax Tmax


Cmax = C [drug]max in BLOOD.
Cmax is a beautiful concept to understand. For ex., as an RN, you know the peak time of Humalog/Novolog is about 1.5hr-2hr. This means this would leave the pt most at risk for hypoglycemia 1.5-2hr after insulin administration. Therefore, if suspecting or worrying, you should check the patient 1.5-2hr for blood sugar after insulin adminstration time. When was an RN student (like a long time ago), it always bewildered me why for humalog/novolog which lasts for like 4-6hrs but pt is most at risk at 1.5-2hrs afterwards. It turns out that is when the drug is available most in the blood and therefore working very hard to get blood sugar down. Therefore, it's best to check the BS 1-2hrs after BS administration rather than later due to Cmax.

However, Cmax Tmax Useful for IV meds and meds absorbed well. Cmax and Tmax kinda useful for insulin. But insulin is quite different in real life. SubQ Lantus 4 units => lasts about a whole day, not half life or short life. Extended release dose more like that.

Extended-release pills (similarly to Lantus subQ)=> cannot really calculate Cmax or Tmax.

Ex: 20mg Amlodipine to 80y/o pt (if you're idiot enuf to do it!) & pt is naive to this = >u wanna check at Cmax

P.s.: Learning pharmacology makes it fun to read the monographs for drugs! You can understand more.


References for Insulin Tmax:
http://www.drugs.com/ppa/insulin-analogs.html
http://pi.lilly.com/us/humalog-pen-pi.pdf
http://www.rxmed.com/b.main/b2.pharmaceutical/b2.1.monographs/CPS-%20Monographs/CPS-%20(General%20Monographs-%20H)/HUMALOG.html
http://www.accessdata.fda.gov/drugsatfda_docs/nda/99/21017_Humalog_biopharmr.pdf

~Miss Student

bioequivalence

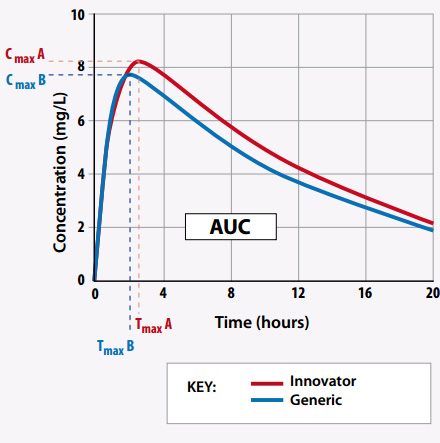
Bioequivalence is different from bioavailability. It compares the Cmax & Tmax of generic drug with innovator drug.

bioavailability

Bioavailability: 

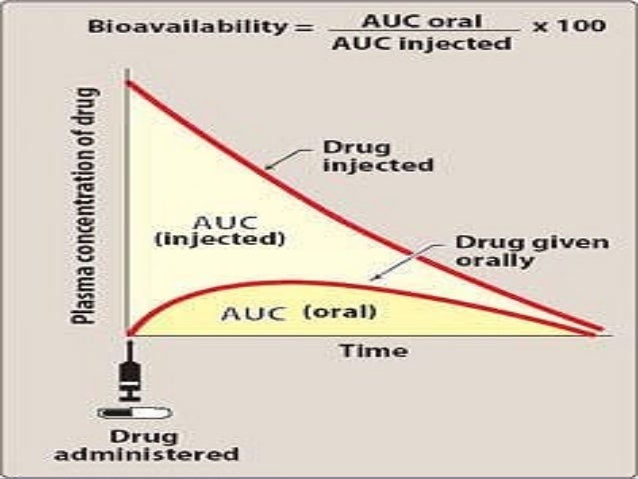
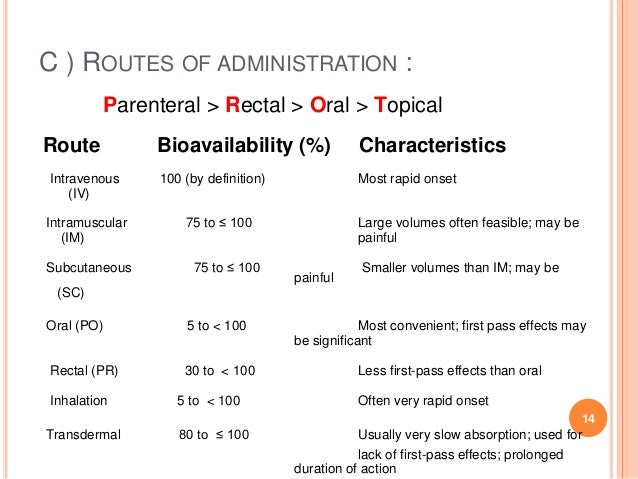
Definition: "Bioavailability of a drug administered intravenously is by definition 100%. Bioavailability is less or equal to 100% for any other route of administration."(1)

Formula: Bioavailability = (AUC oral / AUC iv) x 100%

Clinical implication :
- Use oral bioavailability to calculate needed oral dose. Ex: a drug of 10% oral bioavailability, you'll need an oral dose 10 times of the IV dose (2)

Cite:
(1) http://sepia.unil.ch/pharmacology/index.php?id=51
(2) https://books.google.com/books?id=wYRRAAAAQBAJ&pg=PA5&dq=bioavailability+examples+clinical&hl=en&sa=X&ved=0ahUKEwiRgeSysPHLAhXGs4MKHW1iAKAQ6AEIMTAC#v=onepage&q=bioavailability%20examples%20clinical&f=false

MCQ resources:
 Question #9: 
http://global.oup.com/uk/orc/pharmacy/ifp_therapeutics/student/mcqs/ch01/


MCQ by npprep.blogspot.com - Wonder Me!:
1. What is the bioavailability of Valium IV?:
a. 80%
b. 100%
c. unknown
d. Needs more info.

Correct answer: b. 100%


2. What is the availability of  Oral Lithium?:
a. less than 100%
b. 100%
c. over 100%
d. 60%

Correct answer: a. less than 100%


3. You CANNOT determine bioavailability based on:
a.  urinary excretion of the drug
b.  enteral contents of the drug
c.  plasma contents of the drug
d.  parenteral contents of the drug


Correct answer: b. enteral contents of the drug. Remember: generally, parenteral = IV, plasma ; enteral = PO; urinary excretion = amounts of drug excreted/eliminated

4. An IV drug dose is _____ compared with oral drug dose?
a. smaller
b. larger
c. same
d. non-comparable

Correct answer: a. smaller


5. An oral drug dose is ____ compared with IV drug dose?
a. smaller
b. larger
c. same
d. non-comparable

Correct answer: b. larger


6. What would be the order of greater or lesser bioavailability of the dosage forms?
a. PO > IV > rectal > topical
b. IV > topical > rectal >PO
c.  IV > rectal > PO > topical
d. IV > PO > rectal > topical

Correct answer: c.  IV > rectal > PO > topical


7. Oral bioavailability is NOT dependent on:
a. dosage
b. first pass effect
c. water solubility
d. lipid solubility
e. protein binding

Correct answer: a. dosage  (remember: bioavailability is a percentage %, so it's not dose-dependent or grams-dependent)

8. Bioavailability is dependent on:
a. pharmaceutical formulation
b. dosage
c. absorption
d. first pass effect

Correct answer: a. pharmaceutical formulation (i.e., PO, rectal, IV, topical, ointment, etc.). Remember: absorption is due to first pass effect. A low bioavailability does NOT always mean low absorption rate. It could be absorbed very well but due to first pass effect, it's all eliminated from the body. Thus, it makes the drug bioavailability smaller.

9.  If a drug has oral availability of 20%. The IV dose is 500mg. What's your oral dose?
a. 1000mg
b. 125mg
c. 500mg
d. 2500mg

Correct answer:  d. 2500mg


10. Food can increase the drug bioavailability:
a. True
b. False

Correct answer: a. True. Remember: grape fruit & meds? 


adulteration

As I was reading the lecture about the Pure Food & Drug act (1906), I came across the word 'adulterated'. ???? Adulterated or Mislabeled = NOT pure => this act prohibits im-pure drugs!